Background: Renal development is particularly vulnerable to preterm birth and adverse intrauterine conditions, which may reduce nephron endowment and increase long-term renal risk. Maternal conditions such as preeclampsia, gestational diabetes mellitus (GDM), and thyroid dysfunction may also affect fetal renal development, even in term pregnancies. Serum creatinine, the most commonly used marker of renal function in neonates, has limited value immediately after birth because neonatal concentrations largely reflect maternal levels. Cystatin C (CysC) and beta-2 microglobulin (β2M) may provide more sensitive information on early renal function and maturation. We aimed to compare CysC, β2M, and renal ultrasound findings in preterm infants, term neonates born to mothers with pregnancy-related comorbidities, and healthy term controls.
Methods: This prospective cohort study was conducted at the Clinical Hospital Centre Rijeka, Croatia, between May 2025 and August 2026, and included 171 neonates: 67 preterm infants, 52 term neonates born to mothers with pregnancy-related comorbidities, including GDM, preeclampsia, and thyroid dysfunction, and 52 term neonates born to healthy mothers. CysC and β2M were measured in umbilical cord blood at birth and again during early postnatal follow-up. Renal ultrasonography was performed to assess kidney volume, morphology, and the presence of pyelectasis. Biomarker and ultrasound findings were compared across the three study groups and interpreted in relation to published reference data.
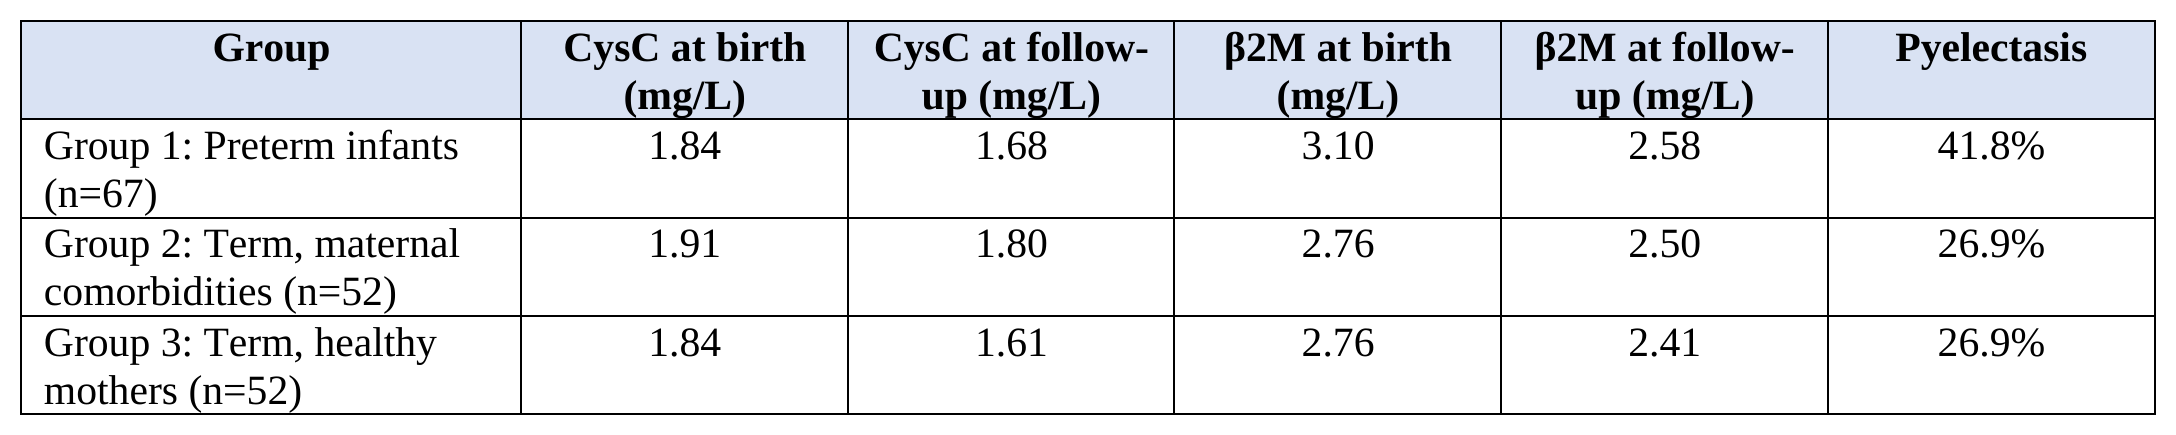
Results: CysC concentrations at birth were comparable across the study groups (median 1.84, 1.91, and 1.84 mg/L in Groups 1, 2, and 3, respectively) and remained within previously reported cord-blood reference ranges. During early postnatal follow-up, however, CysC was highest in term neonates born to mothers with pregnancy-related comorbidities (median 1.80 mg/L), compared with preterm infants (1.68 mg/L) and healthy term controls, who showed the lowest concentrations (1.61 mg/L). In contrast, β2M was highest in preterm infants both at birth (3.10 mg/L) and during follow-up (2.58 mg/L), consistent with its known association with gestational age and renal immaturity. Term neonates exposed to maternal comorbidities demonstrated an intermediate β2M profile at both time points (2.76 mg/L at birth; 2.50 mg/L at follow-up), similar to healthy term controls (2.76 mg/L at birth; 2.41 mg/L at follow-up). Pyelectasis was observed more frequently in preterm infants (41.8%) than in either term group (26.9% in both), while reduced renal volume appeared more common among preterm neonates and infants born to mothers with GDM.
(Table 1)
Conclusions: CysC and β2M demonstrated distinct patterns during early postnatal renal adaptation. β2M appeared to primarily reflect gestational maturity, with persistently higher concentrations in preterm infants. In contrast, CysC remained higher during follow-up in term neonates exposed to maternal pregnancy-related comorbidities, suggesting that an adverse intrauterine environment may influence renal maturation independently of prematurity. These findings support the potential value of combining biochemical biomarkers with renal ultrasonography for early identification of neonates at increased renal risk. Longitudinal follow-up is warranted to determine whether these early alterations persist and whether they are associated with subsequent impairment of renal function or the development of arterial hypertension.